So many things have been happening it’s hard to keep my head spinning at the same rate as events.
In the run up to her MHA Section 2 ending, the consultant must have decided that it was time for J stop wearing the seclusion gown (a special type of patient safety clothes) and to go back to wearing her pyjamas, like other patients on the ward. Nurses had a couple of discussions with her. Both times J said that she didn’t feel safe from herself. Triggering remarks included the mention that other patients shouldn’t have to see the impetigo on her legs and the burn bandage on her arm. J has serious negative body issues as it is. Then they insisted that they were returning the pyjamas to her anyhow, no matter what they said. They put the pyjamas on a shelf in her room and left. Shortly after J was found ligaturing with the pyjama bottoms around her neck. Later in a meeting with myself a nurse told me that the it had been “an acceptable risk” and that they “have to try these things”. I was pressing for decisions to be held back until J’s named nurse is present, and that when J shares her perception on risk that it is not a threat. Again, to J, this was an invalidating experience which somehow confirmed to her that she would be better off dead, especially since they were providing an opportunity.
In the meantime there were a few positive two-way chats with staff (including a service manager), but why do we need such near-miss situations in order to get to that stage of sharing. Patient centred care, my arse.
Suffice the say, the Section 2 ended and she was passed onto a Section 3 (up to 6 months). Again the doctors managed to do this in the clumsiest way ever. After five weeks of refusing to increase a low dose of a replacement anti-psychotic, the consultant finally admits to J that he doesn’t believe that she currently hears voices or hallucinates. They also said that she was going to be assessed and promptly sent to a specialised institution (Cambian again, Birmingham, PD specialists, 1-2 year stay). Naturally this was devastating and triggering. Fortunately this locum is in the process of leaving and good riddance to him. The other doctor was from a crisis team (surprise, surprise, the most prejudicial of all types of consultant). I pointed out of the phone to the AMP/social worker/CPN that, although I agreed to her being kept safe on the ward, that the Cambian residential stay was an old idea which both I and J have reservations about. Also with J challenging her diagnosis of BPD it may turn out to be a totally inappropriate referral. The AMP then managed to get the doctors to agree that the selection of services would be offered. In the meantime J constructed an argument that she was already being compliant with treatment on the ward and that there was still much to finish there. S3 has a “compulsory treatment” element. Both of us are unhappy that an original condition of her stay in hospital was for a complete drugs overhaul and that this had not occurred. This plan was even kept on hold by the locum, who didn’t believe that J needed medication at all. Much as I despise the Bradgate Unit for it’s lack of specialised therapists and dehumanizing battery-farming response to acute patients, H- Ward has been redeeming itself. All this is despite bullying from another patient and a list of day-to-day triggering problems (the pharmacy stopping drugs, attitudes of agaency staff, flaunting of basic privacy etc.).
J has been to Hell and back recently, sometimes begging to be let off the ward so she can end her own life (resulting in being called “selfish” twice by one nurse). I’m amazed she has any fight left in her, whilst still being suicidal.
Yesterday she was assessed by a worker from Cambian and she is now fixated with the not unreasonable notion that she’ll be whisked away suddenly and because of the Section 3.
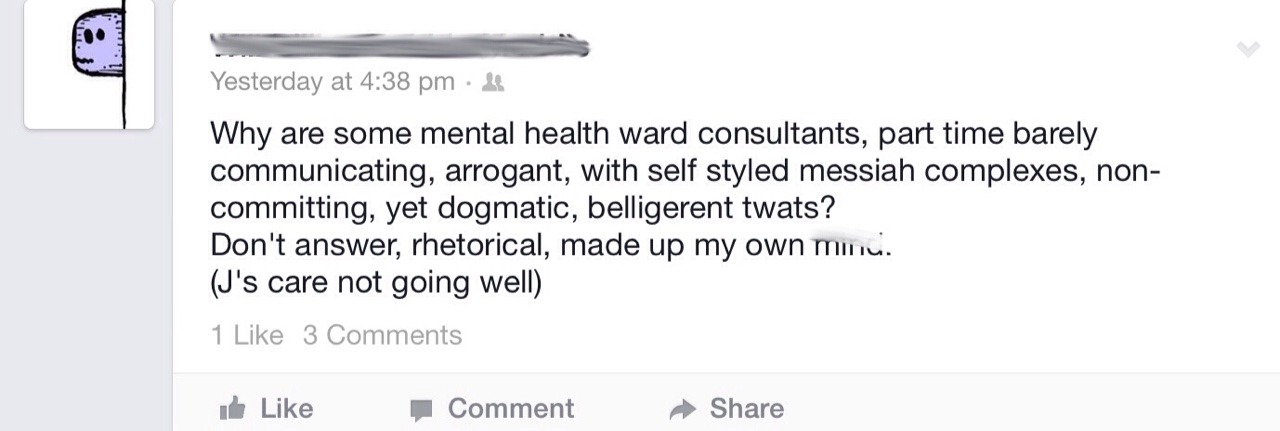
I’ve come to the conclusion that all of the good professionals in her life spend 80 percent of their time repairing the damage caused by bad professionals. I’m also convinced that most psychiatric ward consultants are arrogant sociopaths. So much time and heartache is wasted on every ward stay because of her anxious responses to poor practice. I’m exhausted by trying the piece together the ongoing crime scene and calming her down, or arguing with her about things that might not be the best things to say to staff - for example, some stupid staff interpret explanation of SI and suicide plans as threats. Fortunately a majority of the shifts now have staff which have earn’t J’s trust. What really smarts for me is that when I was asked my opinion by a doctor a few weeks back, he was just assuming that I was being J’s puppet. Sometimes we need plain speaking as early as possible so we can get a second opinion and not waste time. That’s the good news, J is hoping to get a second opinion from a new doctors. There’s way too many “what ifs…?” at the moment.
Oh, and now the locum is leaving, the anti-psychotic drug has been put up to a useful level.
In my other life my concentration is now totally shot. Most of the time she is “safer” but not “safe”. Every other phone call might be news of her death as far as I am concerned. Lucy-cat is becoming my own positive prevention, i.e. to keep it together, stay well for both of them. I’m so tired of ignorant professionals. When nurses get to know her, they find her likeable and actually not all that complicated. So I have to blame the patient notes, a pile of meaningless Chinese whispers and generalisations passed between overpaid part-timers (the doctors).